Does sleep training work? Yes, for most families with babies about 4 months and older, it improves infant sleep in the short to medium term without long-term harm, and also without long-term magic. A 2018 evidence review in Canadian Family Physician found that about 1 in 4 to 1 in 10 babies benefit compared with no sleep training, and the longest follow-up (Price et al., Pediatrics 2012) found no lasting effects at age 6, positive or negative. If you have heard that sleep training is either scientifically proven magic or harmful, both are misreadings of the research.
Key Takeaways
There is strong evidence sleep training improves sleep. In randomized trials of babies 4 months and older, formal sleep training improves both infant sleep and parent mental health without measurable long-term harm.
Compelling safety data: Price 2012 followed sleep-trained children for 5 years and found no differences from controls on attachment, behavior, or cortisol patterns.
The 2012 Middlemiss cortisol paper is often cited as evidence against sleep training, however uncertainty arises as it had only 25 babies, no control group, and 2 days of cortisol data.
The evidence is most compelling for graduated approaches like the Ferber method, controlled crying, and bedtime fading.
Sleep training research by the numbers
1 in 4 to 1 in 10: how many infants benefit from sleep training compared with no sleep training, with no adverse effects reported after five years (Korownyk and Lindblad, Canadian Family Physician 2018).
4% vs 14%: severe parent-reported sleep problems six weeks after a behavioral sleep program, versus usual care, in 235 families with babies 6 to 8 months old (Hall et al., BMC Pediatrics 2015).
No difference at age 6: in 225 followed-up families, no harm to behavior, stress, attachment or parent-child closeness, and no lasting sleep benefit either; the authors concluded the techniques have “no marked long-lasting effects (positive or negative)” (Price et al., Pediatrics 2012).
12 to 16 hours: the total sleep per 24 hours, naps included, that the American Academy of Sleep Medicine recommends for babies 4 to 12 months (Paruthi et al., 2016). It makes no recommendation for babies under 4 months.
Timeline of sleep training research findings
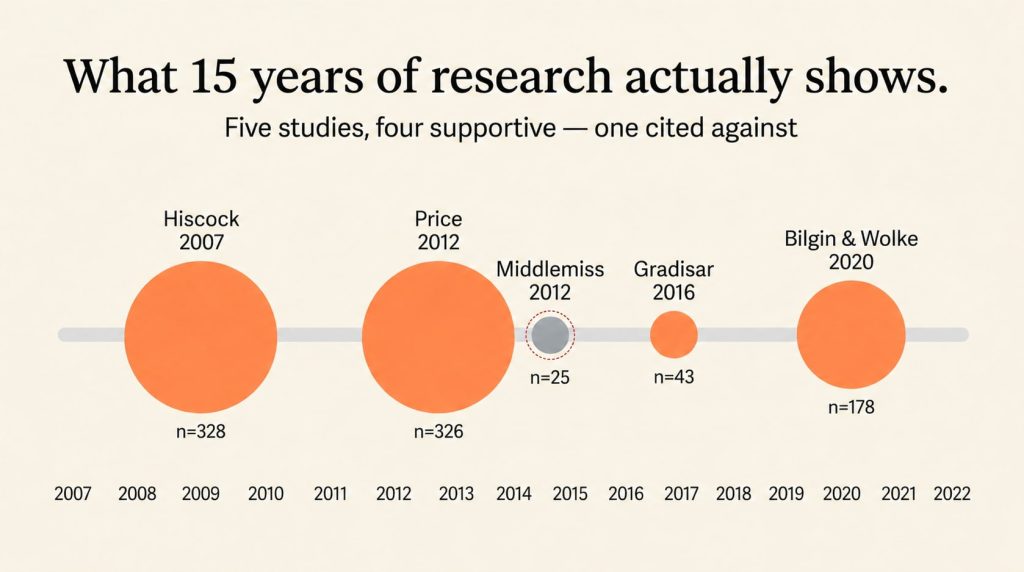
Roughly 30 randomized or controlled trials exist on behavioral sleep interventions in infancy, plus a handful of long-term follow-ups. Five do most of the heavy lifting in public conversation – four supportive, one repeatedly cited against. This is designed to provide reassurance of the evidence we have on that question.
Table of Contents
What 4 major sleep training studies actually found
Hiscock et al., 2007 (BMJ) – cluster RCT, n=328
What it found: Sleep training in 7-month-olds reduced both baby wake-ups and maternal depression at 12-month follow-up. The biggest effect was on mothers, not babies.
A cluster-randomized trial across 49 health centers in Melbourne. 328 mothers of 7-month-olds with reported sleep problems were randomized to a controlled-crying or camping-out intervention, or to usual care. At 12 months, the intervention group had fewer sleep problems and significantly lower maternal depression rates.¹ Controlled crying is the same family of graduated approach the Ferber method is built on – one of several common sleep training methods parents consider. Most pro-sleep-training writing buries the maternal-mental-health finding, but it’s the headline.
Price et al., 2012 (Pediatrics) – 5-year follow-up of the Hiscock cohort
What it found: Five years later, sleep-trained children were indistinguishable from controls on attachment, behavior, cortisol, and emotional wellbeing. This is one of the most reassuring pieces of evidence we have on the question of is it causing harm.
Followed the same cohort up at age six (326 children selected, 173 from the intervention arm). Researchers measured emotional and behavioral functioning, parent-child closeness, disinhibited attachment, cortisol, and child-reported wellbeing. They found no significant differences between groups on any measure² – including no difference on disinhibited attachment, the outcome that addresses the most common worry. The longest and most rigorous follow-up the field has.
Gradisar et al., 2016 (Pediatrics) – RCT, n=43
What it found: Both graduated extinction and bedtime fading improved sleep, lowered cortisol (didn’t raise it), and left attachment unchanged. This is a powerful takeaway in that it is not consistent with the concerns many parents have heard.
Randomized 43 infants (6-16 months) to graduated extinction, bedtime fading, or a sleep-education-only control. Both intervention groups showed significant improvements in sleep latency and night wakings compared with control. Salivary cortisol showed small-to-moderate declines in both intervention groups compared with control.³ At 12-month follow-up, no differences emerged between groups on emotional and behavioral problems or on secure-versus-insecure attachment styles. Smaller sample than Hiscock, but a tighter design – and the cleanest cortisol data we have.
What it found: Families using “cry it out” approaches showed no differences in attachment or behavior at 18 months versus families who didn’t – even when the sample included preterm babies.
A longitudinal observational study following 178 mother-infant dyads (105 full-term and 73 very preterm / very low birthweight) across the first 18 months. Researchers compared families who used “cry it out” approaches with families who didn’t, measuring attachment security and behavioral development at 18 months. They found no adverse effects on either outcome.⁴ Not a randomized trial – but at this sample size, with that endpoint, it adds an independent line of evidence to Price 2012’s 5-year findings on attachment.
Why we trust these four (and one important caveat)
These studies are generally considered more reliable because they use larger samples and, in several cases, randomized designs. Bilgin & Wolke is observational but at a scale that adds useful corroboration to the randomized attachment findings.
One caveat. These studies tested specific protocols – graduated extinction, controlled crying, bedtime fading, camping out. They don’t validate every method called “sleep training” today, particularly more aggressive full-extinction commercial programs. The evidence base is for graduated approaches, not for every sleep training app or program sold under the same label.
Wondering if sleep training is right for your baby?
Take Betteroo’s 3-minute quiz to see what fits your baby, your capacity, and your family.
The one study cited against, and why it can’t carry that weight
Middlemiss et al., 2012 (Early Human Development) – inpatient study, n=25
What the study claimed: On the third day of an extinction-based inpatient program, infants stopped crying behaviorally but their cortisol stayed elevated. Anti-sleep-training pieces interpret this as “hidden distress.”⁵
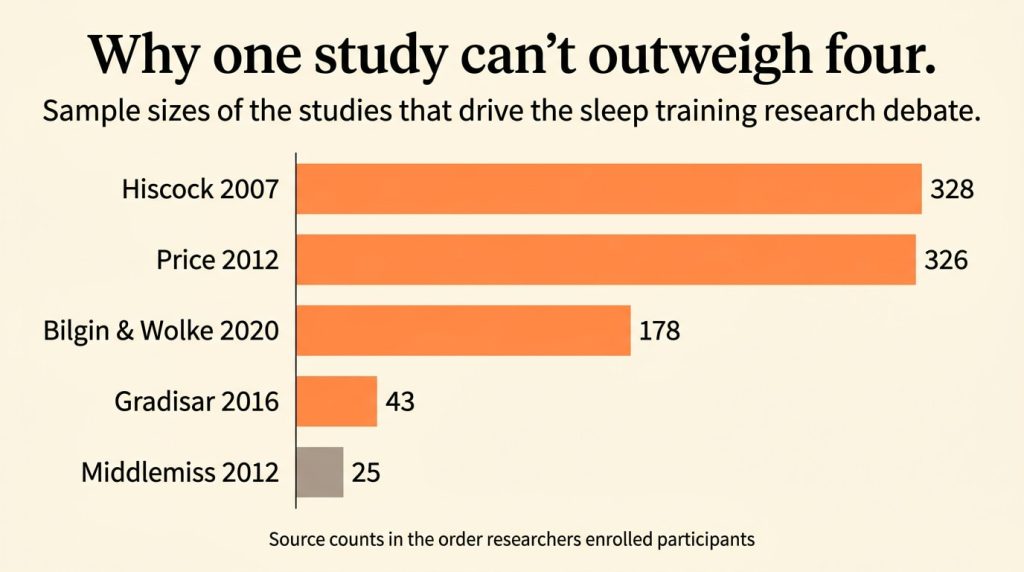
Why it’s important to interpret this study carefully: It’s often asked to answer questions that are larger than what the study itself was designed to address. The study included 25 infants, had no control group, and measured cortisol over a very short window. Because of these limitations, it’s difficult to draw broader conclusions from it on its own.
Sleep training study size comparison
This isn’t a takedown of the researchers. It’s a reminder that one paper of n=25 with no control group cannot tell you whether sleep training is harmful. When a single small study is doing all the persuasive work in a public conversation, that is itself a signal to be skeptical – of the conclusion, not just the study.
Is sleep training safe for my baby?
For a healthy baby about 4 months or older, the best evidence says yes. The randomized trials and their follow-ups found no harm to attachment, behavior or emotional health: Gradisar et al. (Pediatrics 2016) found no differences in emotional or behavioral problems or attachment 12 months after graduated extinction or bedtime fading, and Price et al. (Pediatrics 2012) found no differences at age 6. Price also found no lasting sleep benefit, so the honest summary is “helps now, does no lasting harm, is not a long-term fix on its own.”
Safety also depends on how and when you do it. Every method has to follow the American Academy of Pediatrics safe sleep rules: baby on their back, alone, on a firm, flat, bare surface, with room-sharing but no bed-sharing ideally for at least the first 6 months (AAP 2022 safe sleep policy). Rule out illness, hunger or a medical problem first, and talk with your pediatrician before you start, especially if your baby was premature, has reflux or has trouble gaining weight. See our guide to when to start sleep training for the age questions.
What the AAP actually says about sleep training
The American Academy of Pediatrics has no formal policy statement on sleep training. What it does publish, on its parent site HealthyChildren.org, is guidance on self-soothing, and that article draws a clear line: helping a baby learn to fall asleep on their own is not the same as making a baby “cry it out” or ignoring their cries, which it calls “absolutely not true.” The article does not use the term sleep training at all.
The formal clinical guidance comes from the American Academy of Sleep Medicine. Its 2006 practice parameters (Morgenthaler et al., Sleep) rated unmodified extinction, extinction with parental presence and preventive parent education as standards, rated graduated extinction, bedtime fading with positive routines and scheduled awakenings as guidelines, and found insufficient evidence to favor one therapy over another. The AAP’s own journal, Pediatrics, published two of the key trials above (Price 2012 and Gradisar 2016). So when someone says “the AAP recommends” or “the AAP warns against” sleep training, ask for the link: there is no such statement.
What the research can’t tell us
Almost all sleep-training research is on babies older than four months – there’s little evidence base for younger infants, and most pediatric experts agree formal sleep training isn’t appropriate before that age regardless. Most studies measure outcomes in weeks or months, not years; the longest follow-up the field has is Price 2012 at five years. Few studies compare methods head-to-head, so we can’t say Ferber works better than bedtime fading or the chair method – most claims about method superiority track consistency of execution, not the protocol.
Baby temperament as a moderator is barely studied – clinicians know some babies respond easily and others don’t, but the literature mostly ignores it. The cortisol question is genuinely unsettled – other studies (Gradisar 2016³; Hall et al. 2015⁶) have found no cortisol elevation after sleep training. The picture is messy and underpowered, not closed.
Frequently asked questions
Is sleep training safe?
For babies 4 months and older, the largest randomized trials and a 5-year follow-up found no measurable harm. The evidence base is for graduated approaches – controlled crying, bedtime fading, the chair method – not aggressive full-extinction commercial programs. Under 4 months, formal sleep training isn’t appropriate regardless of method.
Does sleep training cause attachment problems?
The best available evidence does not show this. Price 2012 specifically measured attachment outcomes 5 years after sleep training and found no differences from controls. Bilgin & Wolke 2020 reached the same conclusion at 18 months in an independent cohort. Two separate lines of evidence, same answer.
What about the cortisol study people keep mentioning?
That’s the 2012 Middlemiss study – 25 babies, no control group, two days of cortisol data, no replication. Other studies (Gradisar 2016, Hall 2015) found no cortisol elevation after sleep training. The cortisol question is genuinely unsettled – not closed in either direction.
What age does the research support sleep training?
4 months and older. There’s almost no evidence base for younger infants, and most pediatric experts don’t recommend formal sleep training before 4 months regardless of method – which is also when many families first hit the 4-month sleep regression. Under 4 months, the work is building conditions – consistent wind-down, day sleep, feeding adequacy – not running a protocol.
What if sleep training doesn’t work for my baby?
It’s a real and underserved subset. Some babies don’t respond to graduated approaches even when parents stay consistent for 14 nights. Three things to consider: switch to a gentler method (some babies do better with bedtime fading than Ferber), check for medical contributors that mimic sleep problems (silent reflux, allergies, sleep-disordered breathing), or wait – some babies physiologically aren’t ready until later. “It didn’t work” is data, not failure.
What does the American Academy of Pediatrics say about sleep training?
The AAP has no formal policy statement on sleep training. Its parent site, HealthyChildren.org, explains that teaching a baby to self-soothe is not the same as cry it out or ignoring cries. Formal clinical guidance comes from the American Academy of Sleep Medicine’s 2006 practice parameters, and every method must follow AAP safe sleep rules.
Is there real research that sleep training works, or is it just influencers selling courses?
There is real research. Randomized trials such as Hall 2015 (4% vs 14% severe sleep problems) and Gradisar 2016 show short-term gains, and a 2018 review estimates 1 in 4 to 1 in 10 babies benefit. The research tested simple, free methods, not paid programs, and found no long-term harm or long-term benefit.
Key takeaway
If you read one sentence from the research: in randomized trials with babies four months and older, formal sleep training improves sleep and parent mental health without measurable long-term harm. There are real gaps, and babies who don’t respond to any protocol. But the case that sleep training is intrinsically harmful is based largely on a small number of limited studies, rather than the broader body of research. It’s not a perfect answer, but it’s the most balanced one we have right now.
How Betteroo fits
The research supports simple, consistent methods, and consistency is the hard part at 3 a.m. Betteroo builds a sleep plan around your baby’s age and your family’s comfort level, adjusts it when progress stalls, and keeps every caregiver on the same steps. In Betteroo’s State of Parent and Baby Sleep 2026 (October edition), a survey of 83,901 parents who came to Betteroo for sleep help (not a random sample), only 10% said their baby falls asleep independently, so if you are still feeding or rocking to sleep, you are in the majority. Not sure which approach fits? Start with common sleep training methods or read what to do when sleep training is not working.
Still not sure where you stand?
Take Betteroo’s 3-minute quiz for a personalized read on whether sleep training is right for your family – and which approach fits.
Hiscock, H., Bayer, J., Gold, L., Hampton, A., Ukoumunne, O.C., & Wake, M. (2007). Improving infant sleep and maternal mental health: a cluster randomised trial. BMJ, 335(7611).https://pubmed.ncbi.nlm.nih.gov/17158146/
Price, A.M.H., Wake, M., Ukoumunne, O.C., & Hiscock, H. (2012). Five-Year Follow-up of Harms and Benefits of Behavioral Infant Sleep Intervention: Randomized Trial. Pediatrics, 130(4), 643–651.https://pubmed.ncbi.nlm.nih.gov/22966034/
Gradisar, M., Jackson, K., Spurrier, N.J., et al. (2016). Behavioral Interventions for Infant Sleep Problems: A Randomized Controlled Trial. Pediatrics, 137(6), e20151486.https://pubmed.ncbi.nlm.nih.gov/27221288/
Bilgin, A., & Wolke, D. (2020). Parental use of ‘cry it out’ in infants: no adverse effects on attachment and behavioural development at 18 months. Journal of Child Psychology and Psychiatry, 61(11), 1184–1193.https://pubmed.ncbi.nlm.nih.gov/32155677/
Middlemiss, W., Granger, D.A., Goldberg, W.A., & Nathans, L. (2012). Asynchrony of mother-infant hypothalamic-pituitary-adrenal axis activity following extinction of infant crying responses induced during the transition to sleep. Early Human Development, 88(4), 227–232.https://pubmed.ncbi.nlm.nih.gov/21945361/
Hall, W.A., Hutton, E., Brant, R.F., et al. (2015). A randomized controlled trial of an intervention for infants’ behavioral sleep problems. BMC Pediatrics, 15:181.https://pubmed.ncbi.nlm.nih.gov/26567090/
Korownyk, C., & Lindblad, A.J. (2018). Infant sleep training: rest easy? Canadian Family Physician, 64(1), 41.https://cfpclearn.ca/tfp196/
Paruthi, S., et al. (2016). Recommended Amount of Sleep for Pediatric Populations: A Consensus Statement of the American Academy of Sleep Medicine. Journal of Clinical Sleep Medicine, 12(6), 785-786.https://pubmed.ncbi.nlm.nih.gov/27250809/
Morgenthaler, T.I., et al. (2006). Practice parameters for behavioral treatment of bedtime problems and night wakings in infants and young children. Sleep, 29(10), 1277-1281.https://pubmed.ncbi.nlm.nih.gov/17068980/